FACE AND NECK
How Are Face and Neck Lifts Assessed Together?
The lower face, jawline and neck are distinct anatomical areas but closely related in appearance. Some people may therefore have face and neck assessed together; this does not mean both operations must always be performed together.
By Mehti Şalvız
Published:

A facelift and a neck lift are not the same procedure. The midface, lower face and neck have distinct anatomy and assessment considerations. However, the lower face, jawline, submental area and neck are neighbours; a change in one can affect the perceived contour of another.
Regional changes may be more pronounced in the face, neck or jawline in different people. When the lower face–neck transition is prominent, both areas may be examined in the same clinical assessment. This does not automatically place both operations in one plan.
Assessment aims to distinguish whether change is concentrated in the face, the neck or the transition between them. Surgical scope is developed from this anatomical distribution and clinical findings.
Are facelift and neck lift the same procedure?
No. They are distinct surgical topics assessing changes in different anatomical regions. Facelift assessment particularly concerns the midface, lower face, lower cheeks and facial contour extending to the jawline. Neck lift assessment concerns changes beneath the chin, neck skin, soft tissues and neck contour.
The scope of facial surgical assessment is explained on the Facelift Surgery page, and the separate neck assessment framework on the Neck Lift Surgery page. These pages address each region’s anatomical scope individually.
The jawline, where lower face and neck meet, forms a visual transition. Facial changes can affect how neck contour is perceived, and neck changes can affect jawline appearance. This proximity explains why the areas can be examined alongside one another despite being distinct procedures.
Distinguishing procedure names helps identify where findings are concentrated. A facelift focuses on facial contour and a neck lift on neck and submental contour, with the jawline at their intersection. This makes the procedures’ different regional scopes clear.
Why are the lower face and neck related?
Although anatomically separate, face and neck form a continuous visible contour. Lower facial shape, the jawline boundary, submental tissues and the front and sides of the neck can influence one another’s appearance. The jawline is the central boundary joining the facial and neck sides of this transition. Understanding this relationship helps identify where change is most prominent.
Lower face
The lower face includes the lower cheeks, the area below the mouth, chin and transitions towards the jawline. Soft tissue distribution and skin characteristics contribute to the perception of the lower facial boundary. Changes do not occur in the same region or to the same degree in everyone.
A lower facial contour change cannot be explained solely by the neck or reduced to the skin surface. Relationships between the lower cheek, chin and jawline are considered together. Facial findings can then be understood within overall appearance without being confused with separate neck changes.
Jawline
The jawline is perceived as the lower facial boundary while also forming part of the transition into the submental area and neck. It is therefore not an independent line belonging only to face or neck. Lower facial tissue distribution, chin structure and neck contour can jointly affect its visibility.
Assessment does not aim at a fashionable or idealised jaw shape. Within individual anatomy, the jawline is a reference area for understanding the connection between the lower face and neck. Where change is perceived along it can help determine whether facial and neck findings are considered separately or in relation to one another.
Neck region
The neck region begins beneath the chin and extends along the front and side contours. Skin and soft tissue characteristics, submental distribution and the transition from the jawline can affect its visible appearance. Neck changes do not always progress to the same degree as lower facial changes.
The neck is assessed through its own anatomical findings. Because the submental area and jawline connect it to the face, lower facial appearance is also considered. Regional neck changes can then be identified without being confused with separate facial findings.
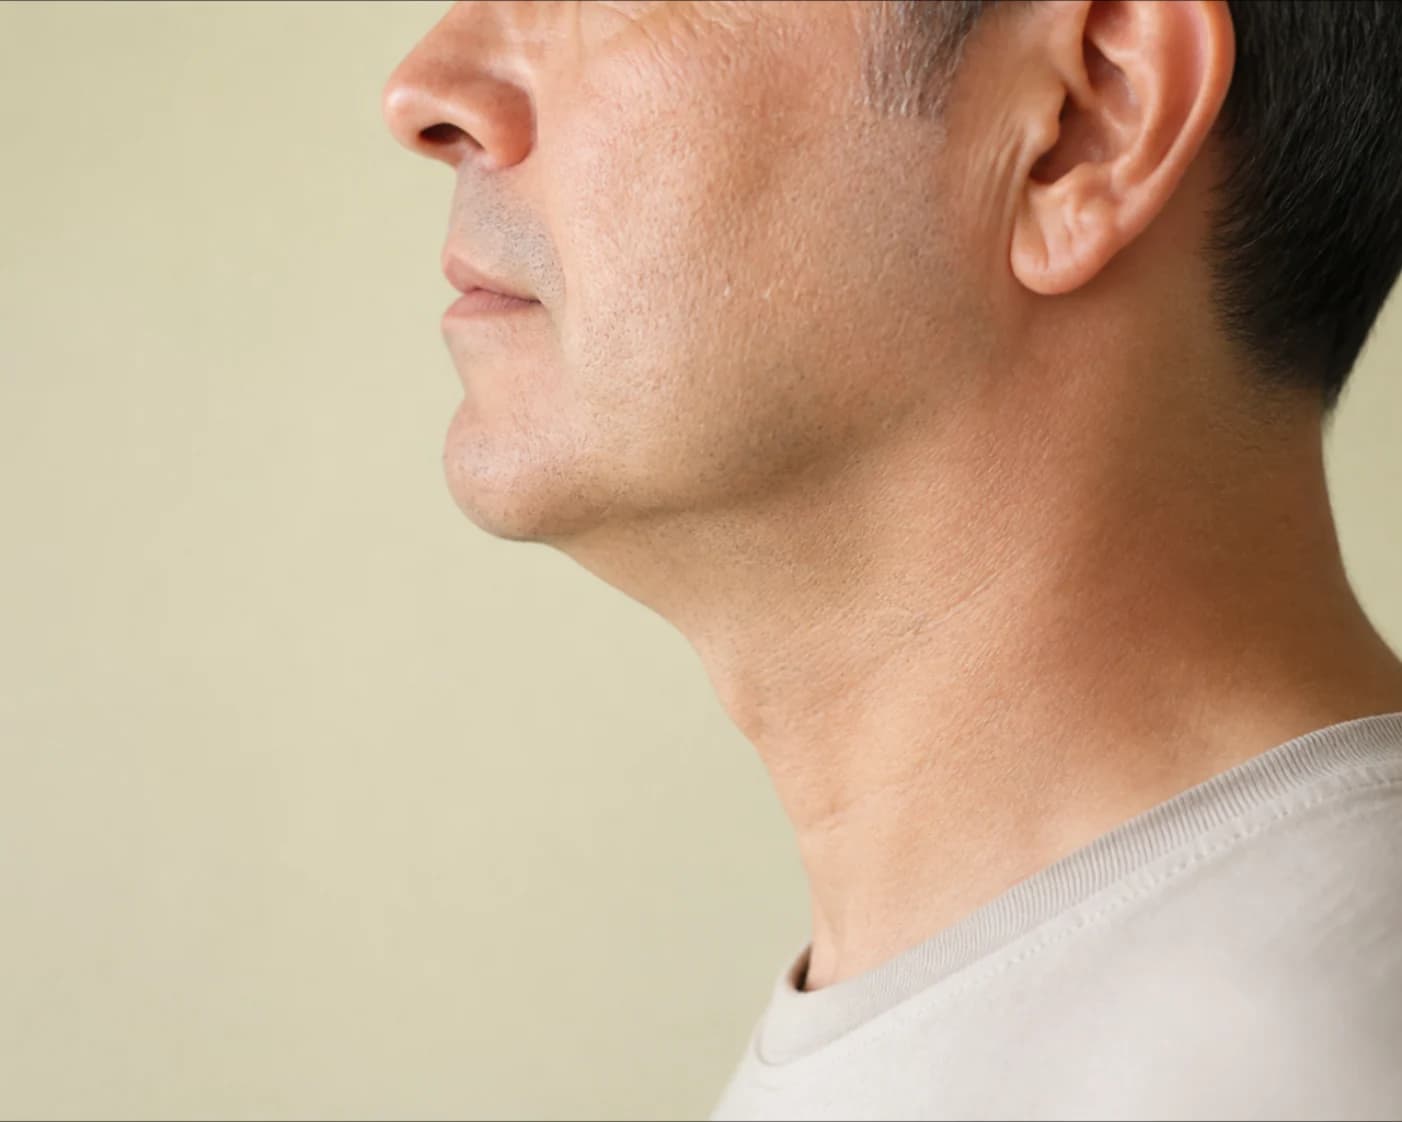
Why is the jawline important in the face–neck relationship?
The jawline can be perceived as the lower facial boundary and is also part of the visual transition where the neck begins. Relationships extending from the lower cheek to the chin and from beneath the chin to the sides of the neck affect how defined or soft it looks. A jawline change is therefore not attributed to one tissue or one region alone.
Changes in lower facial tissue distribution can alter the perceived facial side of the jawline. Submental or neck changes can affect its transition towards the neck. Clinically, the jawline is a connecting area that helps locate changes, rather than an automatic procedural boundary between two surgical areas.
Skin, soft tissue, submental and lower facial causes of neck contour changes are also discussed in the What Causes Neck Sagging? article.
Within individual anatomy, the jawline is a reference area showing how the lower face, submental area and neck connect. The effects of facial and neck changes along it are assessed separately.
Can only the face or only the neck be assessed?
Yes. The face alone, neck alone or both may be considered in one clinical assessment. Changes may concentrate in the midface or lower face, beneath the chin and in the neck, or in regional transitions.
When assessing only the face, the transition to the neck is considered; when assessing only the neck, its transition to the face is considered. Looking at neighbouring areas helps distinguish the origin and regional boundaries of the appearance.
Individual priorities, starting anatomy and the distribution of changes influence which area predominates. Examination identifies facial and neck findings separately before assessing their relationship.
This does not require both operations to be performed together. The plan covers only the region or regions found clinically relevant.
Assoc. Prof. Mehti Şalvız states that he does not operate on the neck when planning midface-only surgery. He considers an isolated neck lift when fullness, skin/platysma laxity or banding predominates in the neck without facial sagging.
What does assessing face and neck lifts together mean?
It means examining the lower face, jawline, submental area and neck within the same clinical assessment. This shows where changes concentrate and how they transition into neighbouring regions.
The lower face forms the contour from the lower cheek to the jawline; the submental area and neck continue below it. Each region’s own findings are identified and their relationships at the boundaries recorded.
Clinical examination identifies separate facial and neck findings, then assesses how they relate around the jawline. This prevents a change in one region from being extended unnecessarily into another, while ensuring that the face–neck contour relationship is not overlooked.
This framework reads face and neck as neighbouring anatomical areas rather than merging their findings into one procedure name. Decisions about surgery depend on the individual findings described in the final assessment section.
The doctor addresses face and neck together when facial sagging contributes to neck appearance. He does not favour an isolated neck procedure that would not provide the expected harmony without a facelift. Assessing both regions together and actually operating on both are distinguished when deciding individual scope.
The approximately 1–2-hour duration and generally same-day discharge for isolated neck surgery are not the totals for combined face–neck surgery. Operating time is not calculated by adding individual procedure times; duration, stay and recovery are explained according to the combined scope.
Does age alone determine surgical planning?
No. Age can provide context in assessing face and neck appearance, but does not alone determine which region is included in a surgical plan. Two people of the same age can differ in facial and neck anatomy, skin, soft tissue distribution and the location of changes over time.
Midface or lower facial changes may predominate in one person, while neck or jawline changes are more prominent in another of the same age. Some may have no condition requiring surgical assessment. Age is insufficient to explain this regional distribution.
Why facial changes cannot be explained by one structure or age alone is discussed in detail in What causes facial sagging? . What matters for planning is not chronological age, but where changes occur within individual anatomy and how they relate.
How is the region to include in surgery determined?
Planning considers the person’s description alongside anatomical findings on clinical assessment. The midface, lower face, lower cheeks, jawline, submental area and front and side neck contours may be examined separately. Assessment considers whether changes concentrate in one region, how they relate to neighbouring areas and how they are perceived within the whole face.
Skin and soft tissue characteristics, baseline face and neck anatomy, previous procedures and general health are also part of the individual framework. They are used to identify which areas are genuinely relevant, not generate an automatic procedure combination. The same description of appearance can correspond to different anatomy in different people.
Once face and neck findings are identified, expectations and assessment priorities are discussed. The face alone, neck alone or their relationship may predominate. General internet information cannot establish the number, extent or combination of areas to include; the decision is based on individual examination and medical assessment.
The broader assessment framework for the face, neck, eye area and upper face is available on the Facial Rejuvenation Surgery page. This places the face–neck relationship within a wider map of anatomical topics.
The final assessment summarises how findings in the midface, lower face, jawline, submental area and neck relate. This anatomical map helps define the boundaries of clinically relevant areas.
The lower face, jawline and neck are neighbouring anatomical areas; planning considers the findings in each region separately.
This content provides general information and does not replace individual medical assessment.